The first week brought loose stools and a slightly metallic taste. Taking it halfway through dinner helped, and my stomach settled after that. I found the routine manageable once I stopped taking it before breakfast.
Nelson Three months 11 Oct 2026Metformin
Metformin helps the body use insulin more efficiently and reduces glucose production by the liver. Metformin tablets are used mainly for adults with type 2 diabetes when blood glucose remains above…
Metformin helps the body use insulin more efficiently and reduces glucose production by the liver. Metformin tablets are used mainly for adults with type 2 diabetes when blood glucose remains above target.
Product information
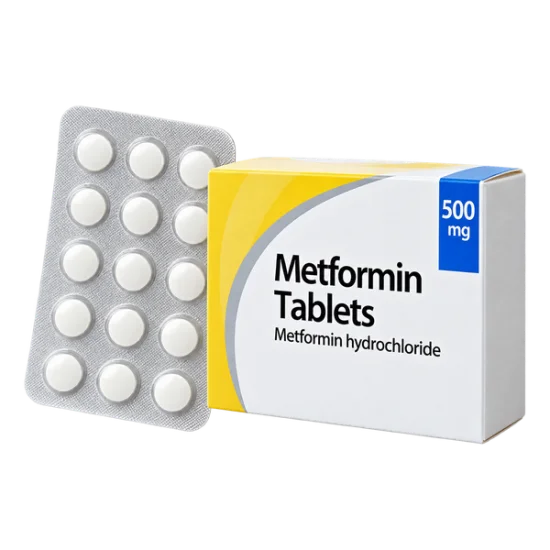
The tablets supplied as Metformin contain metformin hydrochloride as the active ingredient. The active ingredient, metformin hydrochloride, belongs to the biguanide class. The amount taken at each intake is set individually for each person rather than being one fixed amount.
Directions for use
- Take Metformin tablets orally.
- Take the amount prescribed for each intake. The amount is set individually for each person rather than being one fixed amount.
- Take Metformin as part of long-term management of type 2 diabetes, alongside nutrition changes and regular physical activity.
- Metformin is not a replacement for insulin in type 1 diabetes. It may be used with insulin in selected situations and requires individual monitoring because insulin can cause low blood glucose.
Ingredients
The tablets supplied as Metformin contain metformin hydrochloride as the active ingredient. The amount taken at each intake is set individually for each person rather than being one fixed amount.
How it affects the body
Metformin reduces the amount of glucose released by the liver and helps muscle and other tissues respond more effectively to insulin. These effects improve insulin-mediated glucose uptake in peripheral tissues and reduce hepatic gluconeogenesis, so less new glucose is produced between meals and overnight. Metformin does not force the pancreas to release extra insulin.
Therapeutic indications
Metformin hydrochloride is an oral biguanide used to improve blood glucose control in type 2 diabetes. It is often introduced alongside nutrition changes and regular physical activity, then continued as part of long-term diabetes management. Clinical guidance from NICE and the American Diabetes Association (ADA) places metformin among the principal medicines used in type 2 diabetes care [1].
Metformin is not designed to replace insulin in type 1 diabetes. It may be used with insulin in selected situations, but that combination requires individual monitoring because insulin can cause low blood glucose.
Common mistakes
Several practical errors can reduce benefit or increase risk:
- Taking metformin on an empty stomach when it causes digestive symptoms.
- Doubling the next dose after a missed tablet.
- Crushing a modified-release tablet.
- Continuing normal dosing through severe vomiting or diarrhoea without reporting dehydration.
- Ignoring new numbness, tiredness, or anaemia during long-term treatment.
- Forgetting to mention metformin before contrast imaging.
- Drinking heavily while using metformin with insulin or a sulfonylurea.
- Stopping treatment suddenly without a plan for blood glucose monitoring.
One easily missed detail is the difference between a standard tablet and a modified-release tablet. The same active ingredient can require a different schedule, so formulation changes should be made through the prescribed treatment plan.
Reasons not to use it
Metformin is not suitable for everyone. This medicine is not for you if a prescriber has identified a contraindication such as:
- Severe kidney impairment or rapidly worsening renal function.
- Previous lactic acidosis.
- Acute metabolic acidosis, including diabetic ketoacidosis.
- Severe dehydration, shock, or a condition causing inadequate oxygen supply to tissues.
- Severe infection or acute heart or respiratory failure requiring urgent care.
- Serious liver disease where the prescriber considers lactate handling unsafe.
- A known allergy to metformin hydrochloride or an excipient in the tablet.
Pregnancy and breastfeeding require an individual treatment decision. Metformin is used in some pregnancy-related diabetes plans, but the choice depends on glucose targets, pregnancy stage, kidney function, and local clinical guidance.
Specific medicines and procedures can alter risk. These include iodinated contrast, some diuretics, medicines that affect kidney function, and other glucose-lowering treatments. Insulin and sulfonylureas increase hypoglycaemia risk when combined with metformin, even though metformin alone rarely causes low blood glucose. The Medsafe data sheet and local prescribing information provide the clinical framework for these precautions [2].
When this is not for you
Metformin is not suitable for everyone. Tell your prescriber if you have severe kidney problems, serious liver disease, severe dehydration, a serious infection, heart or respiratory failure, or a previous episode of lactic acidosis. Tell the imaging team that you take metformin before a contrast-enhanced scan.
Metformin is generally withheld during significant dehydration, prolonged fasting, or an acute illness that reduces oxygen delivery to tissues. Resumption should follow a specific clinical instruction once normal fluid intake and kidney function are established.
Unwanted effects
Nausea, diarrhoea, abdominal discomfort, bloating, and reduced appetite are among the most familiar adverse effects of metformin. A metallic taste or altered taste perception can also occur. These effects are most common when treatment starts or when the dose increases quickly. Many people experience improvement after the digestive system adapts. Gradual dose escalation, taking tablets with food, and avoiding sudden changes in the prescribed schedule can help. Persistent watery diarrhoea deserves attention because dehydration can impair kidney function and make metformin less suitable temporarily.
Metformin does not usually cause hypoglycaemia when used alone. The risk rises when it is combined with insulin or a sulfonylurea, especially if meals are skipped, alcohol intake is high, or physical activity increases unexpectedly.
A metallic taste is unpleasant but usually not dangerous. Mouth dryness, changes in appetite, and mild stomach discomfort may be easier to manage when tablets are taken during the meal rather than before it. Do not compensate for missed doses by taking two tablets together.
Lactic acidosis is rare but serious. It involves an excessive rise in lactate and acid levels in the blood. The risk increases with substantial renal impairment, severe dehydration, uncontrolled infection, tissue hypoxia, acute heart or respiratory failure, heavy alcohol use, and some situations involving reduced liver function.

Comparison
Metformin is available in standard-release and modified-release tablets. Standard-release tablets release metformin during digestion, while modified-release tablets use a formulation designed to release the active ingredient more gradually.
| Formulation | Release pattern | Practical difference |
|---|---|---|
| Standard-release tablet | Releases metformin during digestion | May require divided doses with meals |
| Modified-release tablet | Releases metformin more gradually | May allow less frequent dosing and improved gastrointestinal tolerance |
| Metformin hydrochloride | Active ingredient in either formulation | Lowers liver glucose production and improves insulin sensitivity |
The release profile affects how often a tablet is taken and whether it can be divided. Standard tablets and modified-release tablets must not be treated as interchangeable without a prescriber’s direction.
What doctors say
In clinical practice, prescribers usually judge metformin by blood glucose trends, glycated haemoglobin, kidney function, tolerability, and the wider diabetes plan. A gradual start is often chosen when the person has a history of digestive sensitivity. The aim is to reach a useful dose without creating diarrhoea severe enough to cause dehydration.
Doctors also distinguish treatment failure from poor tolerability. A person may have acceptable glucose control but stop tablets because of persistent gastrointestinal symptoms. Switching to a modified-release formulation or changing the dose schedule may help, although the specific option depends on the prescribed product.
A patient who misses occasional doses should not double the next intake. Repeated missed doses, frequent illness, or uncertainty about the regimen should be addressed through the diabetes care team because the correct adjustment depends on the person’s glucose results and accompanying medicines.
What customers often ask
Which symptoms mean stopping metformin and seeking urgent medical help?
Severe weakness, repeated vomiting, deep or rapid breathing, marked drowsiness, abdominal pain, feeling unusually cold, or sudden dizziness require urgent assessment because they can signal lactic acidosis or another serious illness. The 2022 FDA prescribing information identifies severe renal impairment, hypoxia, dehydration, and acute illness as important risk settings [3]. Do not take additional doses while waiting for urgent clinical advice if these symptoms occur during severe illness. Emergency symptoms take priority over routine glucose monitoring.
How long does one metformin dose keep working?
Metformin is intended for regular use, not as a short-acting rescue treatment for one high glucose reading. A single dose influences glucose production and insulin sensitivity over part of the dosing interval, while the full treatment benefit depends on repeated doses and changes in glycated haemoglobin over time. The 2025 NICE guidance describes diabetes treatment through ongoing glucose monitoring and scheduled review rather than isolated tablet effects [4]. The duration depends on the formulation, kidney function, meal pattern, and the prescribed schedule.
Is metformin taken with food or on an empty stomach?
Metformin is commonly taken with or immediately after food because meals can reduce nausea, cramping, and diarrhoea. The exact timing depends on the prescribed formulation and whether the regimen uses one or several daily doses. Taking tablets with food does not remove the need to follow the prescribed schedule. The 2023 WHO Model List of Essential Medicines recognises metformin as an oral glucose-lowering medicine used within structured diabetes care [5].
Which diet, exercise, and habits help metformin work better?
Regular meals, appropriate carbohydrate portions, physical activity suited to fitness and medical status, adequate hydration, and consistent sleep can support glucose control. Skipping meals, heavy alcohol intake, sudden intense exercise, and prolonged dehydration can make glucose levels less predictable or increase treatment risks. Metformin works alongside these habits rather than replacing them, as reflected in the 2025 NICE guidance. Weight changes, illness, and changes in activity may require a review of the wider diabetes plan.
What happens when metformin is stopped, and does it need tapering?
Stopping metformin can allow liver glucose production and blood glucose levels to rise again, especially when no alternative treatment is in place. Metformin itself does not usually require a gradual taper for withdrawal symptoms. A prescriber may still recommend a planned change because glucose monitoring and replacement treatment may be needed, as reflected in 2025 NICE guidance. Stopping during severe dehydration or an acute illness is a safety decision that should be followed by a clear restart plan.
What should be checked before starting metformin?
Kidney function should be assessed before treatment, with eGFR used to guide suitability and dosing. The prescriber should also review liver disease, heart or respiratory failure, dehydration risk, alcohol intake, planned contrast imaging, pregnancy, breastfeeding, and all glucose-lowering medicines. A history of lactic acidosis or diabetic ketoacidosis is highly relevant. These checks help identify patients who need a different treatment plan or closer monitoring, consistent with 2025 NICE guidance.
Can people under 18 use metformin?
Metformin may be prescribed for some children and adolescents with type 2 diabetes, but paediatric use requires age-appropriate assessment, dosing, monitoring, and follow-up. The diagnosis must be established because type 1 diabetes, monogenic diabetes, and other conditions require different treatment. Weight, kidney function, puberty, nutrition, and family support may affect the plan. Paediatric prescribing should follow specialist guidance and Medsafe information published in 2023.
Do you offer anonymous delivery?
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.
Comparison
Standard Tablets and Modified-Release Formulations
Metformin is available in standard-release and modified-release tablets. The product described here is a 500 mg tablet presentation. Standard-release tablets release metformin during digestion, while modified-release tablets use a formulation designed to release the active ingredient more gradually.
Pharmacokinetic Differences in Release Rates
After oral administration, metformin reaches the gastrointestinal tract and is absorbed into the bloodstream. It is not extensively metabolised by the liver. The kidneys remove most of the drug, so reduced renal function can increase exposure and raise the risk of accumulation.
Long-Term Nutritional Considerations and Vitamin B12 Status
Long-term metformin use can reduce vitamin B12 concentrations in some people. The effect may relate to altered intestinal absorption and may be more relevant with higher doses, longer treatment duration, older age, anaemia, neuropathy, or other factors that already increase the risk of deficiency.
Possible B12 deficiency features include persistent tiredness, a sore or smooth tongue, pale skin, numbness, pins and needles, balance changes, or worsening nerve symptoms. Diabetes itself can also cause neuropathy, so a new or changing symptom should not automatically be attributed to blood glucose.
Periodic B12 testing is useful when metformin is taken for several years or when symptoms or risk factors are present. If deficiency is confirmed, clinicians can treat it while deciding whether metformin should continue.
How Buyers Rate Metformin
Based on 5 reviews
My glucose readings improved gradually rather than overnight. I missed one tablet and took the next scheduled dose instead of doubling it. The early nausea was frustrating, but it became much less noticeable after the dose was changed.
Lower Hutt First month 19 Oct 2026Metformin had been part of my diabetes routine for years. A blood test found low B12 after I mentioned tingling in my feet. Treating the deficiency helped, although the foot symptoms did not disappear immediately.
Tauranga Long-term treatment 26 Oct 2026The medicine was useful for my readings, but diarrhoea returned whenever I increased the dose too quickly. My prescriber changed the schedule, and I now pay more attention to hydration during hot weather.
Levin 3 Nov 2026Metformin alone did not cause low sugars for me. That changed when another diabetes medicine was added, so I learned to recognise shaking and sweating. The combination worked better, but it required more planning around meals.
Napier 9 Nov 2026Sources
- National Institute for Health and Care Excellence (NICE) (2025). Type 2 diabetes in adults: management, NICE guideline NG28.
- Medsafe (2023). Metformin hydrochloride: New Zealand data sheet and prescribing information.
- U.S. Food and Drug Administration (FDA) (2022). Metformin hydrochloride prescribing information.
- National Institute for Health and Care Excellence (NICE) (2025). Type 2 diabetes in children and young people: management, NICE guideline NG18.
- World Health Organization (WHO) (2023). WHO Model List of Essential Medicines.